NET, NEN and NEC are not interchangeable
Neuroendocrine neoplasm (NEN) is an umbrella term. It includes:
- neuroendocrine tumours (NETs), which are well differentiated; and
- neuroendocrine carcinomas (NECs), which are poorly differentiated and usually behave more aggressively.
Differentiation describes how much the cancer cells resemble the normal cells they came from. It is separate from stage.
Older reports or conversations may use terms such as carcinoid. Classification has changed as understanding has improved, so the exact wording on the pathology report matters.
Where did it start?
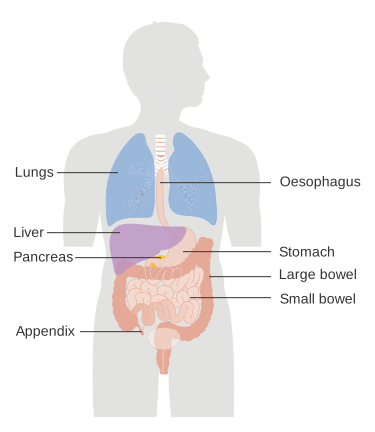
The primary site influences staging, likely behaviour and treatment. A pancreatic NET and a small-bowel NET may share neuroendocrine features but are not managed as if they were identical.
Sometimes the primary site is not clear when cancer is first found. Imaging, endoscopy, pathology and specialised scans may help identify it. In some cases it remains unknown.
What do grade and Ki-67 mean?
Grade describes biological behaviour, including how quickly the tumour cells appear to be dividing. Ki-67 is a marker used by the pathologist to estimate the proportion of cells in the growth cycle.
These results need to be interpreted with the differentiation, primary site and biopsy sample. The separate article on NET grade, stage and Ki-67 explains these terms in more detail.
Functioning and non-functioning NETs
Some NETs release enough hormone or a hormone-like substance to cause a recognisable group of symptoms. These are often described as functioning NETs.
Others do not produce a clinical hormone syndrome and are called non-functioning. Non-functioning does not mean inactive or harmless. It refers to hormone-related symptoms, not whether the tumour is growing.
Symptoms vary with the primary site, hormone production and extent of disease. Many symptoms have much more common non-cancer causes, so symptoms alone cannot diagnose a NET.
How are treatment decisions made?
The multidisciplinary team may consider:
- the primary site;
- whether the cancer is a well-differentiated NET or a poorly differentiated NEC;
- grade and Ki-67;
- stage and distribution of disease;
- whether hormones are causing symptoms;
- findings on specialist imaging;
- previous treatment, general health and personal priorities.
Options can include surgery, medicines that control hormone effects, somatostatin analogues, targeted drugs, chemotherapy, peptide receptor radionuclide therapy, liver-directed treatment, radiotherapy or active surveillance. The appropriate list is different for different neuroendocrine cancers.
Questions that clarify the diagnosis
- Where is the primary site?
- Is this a NET or a neuroendocrine carcinoma?
- What are the differentiation, grade and Ki-67?
- What is the stage?
- Is it functioning or non-functioning?
- Has the case been reviewed by a specialist neuroendocrine multidisciplinary team?
Those details are more useful than the word neuroendocrine on its own. They explain why people with neuroendocrine cancer can receive very different treatment recommendations.


